
Permanent seed brachytherapy
What is permanent seed brachytherapy?
Permanent seed brachytherapy, also known as low dose-rate (LDR) brachytherapy, is a type of internal radiotherapy where tiny radioactive seeds are put into your prostate. Each radioactive seed is the size and shape of a grain of rice.
How does it work?
The seeds stay in the prostate forever and give out a steady dose of radiation over a few months. This damages the cancer cells causing them to die. But healthy cells can repair themselves more easily.
The seeds release most of their radiation in the first three months. After around 8 to 10 months, almost all the radiation has gone.
You may also have heard about a different type called high dose-rate or temporary brachytherapy. During this type of brachytherapy, the source of radiation is temporary and only in the prostate for a few minutes. Find out more.
Download or order our permanent seed brachytherapy fact sheet
Who can have permanent seed brachytherapy?
Permanent seed brachytherapy is suitable for some men with localised or locally advanced prostate cancer. It may be given on its own or alongside other treatments, depending on the risk of your cancer spreading. You may hear this called your Cambridge Prognostic Group (CPG).
Not all hospitals offer brachytherapy, but you can be referred to one that does. This may mean you need to travel for your treatment.
Permanent seed brachytherapy on its own
If you have localised prostate cancer that has a low risk of spreading (CPG 1 or 2), you can have permanent seed brachytherapy on its own.
For low-risk localised prostate cancer, permanent seed brachytherapy works as well as surgery or external beam radiotherapy.
Some men can have permanent seed brachytherapy on its own if they have medium-risk localised prostate cancer (CPG 3). But we don’t have as much evidence about how well it works on its own for this type of prostate cancer. Or you might be offered permanent seed brachytherapy with other treatments.
Permanent seed bracytherapy with other treatments
If you have localised prostate cancer that has a higher risk of spreading (CPG 4 or 5), or locally advanced prostate cancer, you may have it alongside external beam radiotherapy or hormone therapy (or both).
This is called a brachytherapy boost. There’s evidence that it can make the other treatments more effective, but there is an increased risk of side effects.
When might permanent seed brachytherapy not be suitable?
Permanent seed brachytherapy may not be suitable if for everyone. For example, it's not an option for those with advanced prostate cancer. It may also not be recommended if you have a large prostate, urinary problems, or inflammatory bowel disease (IBD). This is because it can make these problems worse.
If you’ve had a transurethral resection of the prostate (TURP), you may have to wait at least three months before having permanent seed brachytherapy. tI may not be suitable if the TURP has created a large opening in the prostate.
What are the advantages and disadvantages?
What may be important to one person might be less important to someone else. So speak to your doctor or nurse about your own situation. You may find our list of questions helpful.
If you’re having external beam radiotherapy or hormone therapy as well as permanent seed brachytherapy, think about the advantages and disadvantages of those treatments as well.
Recovery is quick. Most men can return to their normal activities one or two days after treatment.
By putting radioactive seeds straight into the prostate, a higher dose of radiation can be focused on the cancer cells while reducing the impact on nearby organs, like the bladder and bowel.
With less damage to surrounding healthy tissue, there is a lower risk of some side effects, including urinary incontinence and erection problems.
You will only be in hospital for one or two days.
If your cancer comes back, you can still have further treatment.
It can cause side effects such as urinary, erection, and bowel problems.
It may be some time before you know whether the treatment has been successful.
You will need a general or spinal anaesthetic, which can have side effects.
The level of radiation given out by the seeds is low and you’re not a risk to the general public. But for the first two months, avoid a lot of close physical contact with children, pregnant women and pets. Read more about radiation safety.
What does the treatment involve?
Each hospital may do things slightly differently, but you will usually have:
an appointment to check if the treatment is suitable
a planning session
the treatment itself.
Your first appointment
At your first appointment, you’ll usually have a scan to check the size of your prostate and find out how many seeds you’ll need. This is called a volume study.
If your prostate is too large, you may be offered hormone therapy for up to six months to shrink it before the treatment.
Very rarely, the prostate's position may mean permanent seed brachytherapy is not suitable. If this happens, the specialist will discuss other treatment options with you.
You'll usually have your planning session two to three weeks later.
Before the planning session, tell your specialist about any medicines you take, especially medicines that thin your blood such as aspirin, warfarin or clopidogrel. Don’t stop taking any medicines without speaking to your doctor or nurse.
Planning session
Most hospitals plan and put in the seeds on the same day (a one-stage procedure). Others do this on separate days (a two-stage procedure).
The planning session takes about 30 minutes. An ultrasound probe is placed in your back passage to create a detailed image of your prostate. This shows where to put the seeds.
You may need a laxative the day before, or an enema at the hospital, to empty your bowels and help produce a clear scan.
You will usually have a general anaesthetic, so will be asleep during the scan. If this is not suitable, you may have a spinal anaesthetic (epidural). This means can’t feel anything from the waist down.
You may also have a catheter, a thin tube passed through the tube you urinate through, to drain your bladder.
You can go home on the same day if you’re not having the treatment straight away. Ask a friend or family member to take you home, as you shouldn’t drive for at least 24 hours after an anaesthetic.
Placing the seeds
If treatment on the same day as your planning session, the seeds will be put in straight after the scan, under the same anaesthetic. If your treatment on a different day, you’ll need another anaesthetic and might also need to take another laxative or have another enema to empty your bowels.
Depending on the size of your prostate, between 60 and 120 seeds are put into the prostate using around 15 to 30 needles. The seeds can be loose individual seeds or linked in a chain using material that slowly dissolves. The type of seed you have will depend on the hospital.
The treatment usually takes 45 to 90 minutes. During the treatment, an ultrasound probe will be put inside your back passage again to help make sure the seeds are put in the right place. In some hospitals, the doctor will put gel into your urethra instead of a catheter, so they can see your urethra more clearly and avoid putting any seeds into it.
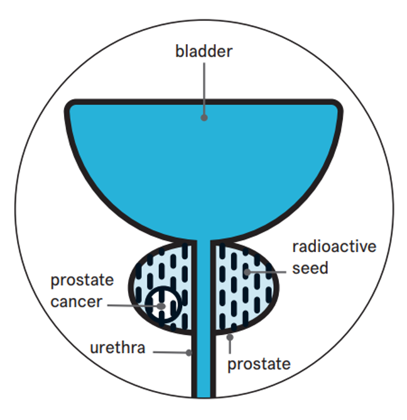
The oncologist or urologist will then put long thin needles through your perineum (the area between the testicles and back passage) and into your prostate. The radioactive seeds are passed through the needles into the prostate. The needles are then taken out, leaving the seeds behind.
Where the seeds go in the prostate
After your treatment
You'll stay in hospital for a few hours after treatment while you recover from the anaesthetic. Most men go home the same day, once they can pass urine, although some may need to stay overnight. You shouldn’t drive for 24 hours after the anaesthetic, so arrange for someone to take you home.
If you had a catheter, it's usually removed before you wake up or later that day. Having the catheter removed may be uncomfortable, but it shouldn’t be painful.
Your doctor or nurse will give you any medicines that you need at home. These may include drugs to help you urinate, antibiotics to prevent infection, and pain relief.
Going back to normal activities
Most men return to your normal activities after a few days. But it's best to avoid heavy lifting for the first few days. Speak to your doctor, nurse or radiographer about your own situation.
When should I call my medical team?
Your doctor, nurse or radiographer will give you a number to call if you have any questions or concerns. Contact them if have any of the following:
Your urine is very bloody or has large clots in it, you may have some bleeding in your prostate. Contact your doctor or nurse as soon as possible.
You suddenly and painfully can’t urinate, you may have acute urine retention.Go to your local A&E department, as this needs urgent treatment. Take details of your cancer treatment with you if possible.
If you have a high temperature (above 38ºC or 101ºF), this may be a sign of infection. Contact your doctor or nurse, or go to your local A&E department.
Your follow up
You’ll have an appointment with your doctor, nurse or radiographer four to six weeks after your treatment. They will check how well you’re recovering, your PSA level (see below), and ask about any side effects.
You might also have a CT or MRI scan to check the position of the seeds. This can happen on the same day as your treatment, but it may be up to six weeks after your treatment, depending on your hospital.
PSA blood test
You’ll usually have a PSA test six weeks after your treatment. Then, for the next two to three years, you'll have a PSA test every six months, then once a yearly.
Some hospitals may not offer regular follow-up appointments. Instead, you may get your PSA results by phone, letter or from your GP. You'll be told who to contact if you have any questions or concerns.
Your PSA level should steadily drop over the next five years. How quickly it falls, and how low it goes, varies from man to man. It won’t fall to zero because healthy prostate cells produce some PSA.
Your PSA level may rise after your treatment, then fall again (PSA bounce). This is normal and doesn’t mean your cancer has come back, or need more treatment. It usually happens within 18 months, but it can happen up to three years after treatment. It's more common in younger men and men with a large prostate.
If your PSA level keeps rising, particularly in a short amount of time, this could be a sign that the cancer has come back. If this happens, your doctor will talk to you about further tests and further treatments. You can also contact our Specialist Nurses for information and support.
What are the side effects of permanent seed brachytherapy?
Permanent seed brachytherapy can cause side effects. Side effects affect each person differently, and you might not get all of them. They may include:
bruising (in the area between your testicles and back passage)
Some men develop long-term or late side effects after treatment, but this is rare. This is called pelvic radiation disease and there’s more information on the Pelvic Radiation Disease Association website.
You can read more about side effects, including ways to treat and manage them.
Radiation safety
Most radiation is absorbed by the prostate and surrounding tissue, so It’s safe to be around other people. But for the first two months after treatment:
Avoid being closer than 50 cm to children for more than a few minutes a day. You can give them a quick cuddle, but avoid having them on your lap.
Avoid being this close to pregnant women for long periods of time (more than three hours).
Avoid letting pets sit on your lap.
This is because these groups are more sensitive to radiation, but the risk is still very low.
Cremation after treatment
If a man dies, for whatever reason, in the first 20 months after having treatment, it won't be possible to have a cremation. This is because of the radioactive seeds. Some men decide not to have this treatment because of this – for personal or religious reasons. Speak to your doctor or nurse if you have any worries.
Advice card
You'll be given an advice card that says you’ve had treatment with permanent seed brachytherapy. You should carry this with you for at least 20 months – especially when you travel.
If the seeds move or come out
The seeds usually stay in the prostate, but they can move or come out. If this happens, it’s most likely in the first month. A scan at your follow-up should find this.
If a seed comes out when you urinate
This is very rare. You may feel slight discomfort, but you are more likely to see the seed in the toilet.
If this happens in hospital, leave the seed where it is and let the staff know straight away. If this happens after you’ve left hospital, don’t try to pick it up. Just flush it down the toilet.
If a seed comes out in your semen.
Very rarely, a seed can also come out when you ejaculate. To be safe:
avoid sex for a few days
use a condom for the first five ejaculations after your treatment
double-wrap used condoms and put them in the bin.
Always tell your doctor, nurse or radiographer if you think you’ve passed a seed.
Can seeds move to another part of body?
Very rarely, a seed may travel through the bloodstream to another part of the body. This has not been found to cause harm because it releases only a very small amount of radiation.
Questions to ask your doctor, nurse or radiographer
Will I have a planning session at a different time to the treatment, or immediately before?
Will I have external beam radiotherapy or hormone therapy as well?
What side effects might I get?
How will we know if the treatment has worked?
What should my PSA level be after treatment and how often will you measure it?
If my PSA continues to rise, what other treatments are available?
References and reviewers
Updated: September 2026 | Due for Review: September 2029
Andersen MF, Midtgaard J, Bjerre ED. Do Patients with Prostate Cancer Benefit from Exercise Interventions? A Systematic Review and Meta-Analysis. Int J Environ Res Public Health. 2022 Jan;19(2):2. doi:10.3390/ijerph19020972
Andreyev HJN. GI Consequences of Cancer Treatment: A Clinical Perspective. Radiat Res. 2016 Mar 28;185(4):341–8. doi:10.1667/RR14272.1
Awad MA, Gaither TW, Osterberg EC, Murphy GP, Baradaran N, Breyer BN. Prostate cancer radiation and urethral strictures: a systematic review and meta-analysis. Prostate Cancer Prostatic Dis. 2018 Jun;21(2):168–74. doi:10.1038/s41391-017-0028-3
Bownes P, Coles I, Doggart A, Kehoe T. UK Guidance on Radiation Protection Issues following Permanent Iodine- 125 Seed Prostate Brachytherapy [Internet]. 2012. Available from: https://www.ipem.ac.uk/ScientificJournalsPublications/UKGuidanceonRadiationProtectionIssuesfollowi.aspx
Chao MWT, Grimm P, Yaxley J, Jagavkar R, Ng M, Lawrentschuk N. Brachytherapy: state-of-the-art radiotherapy in prostate cancer. BJU Int. 2015 Oct;116:80–8. doi:10.1111/bju.13252
Chen RC, Basak R, Meyer AM, Kuo TM, Carpenter WR, Agans RP, et al. Association Between Choice of Radical Prostatectomy, External Beam Radiotherapy, Brachytherapy, or Active Surveillance and Patient-Reported Quality of Life Among Men With Localized Prostate Cancer. JAMA. 2017 Mar 21;317(11):1141–50. doi:10.1001/jama.2017.1652
Corey G, Yoosuf ABM, Workman G, Byrne M, Mitchell DM, Jain S. UK & Ireland Prostate Brachytherapy Practice Survey 2014-2016. J Contemp Brachytherapy. 2018;10(3):238–45. doi:10.5114/jcb.2018.76839
Cornford et al. EAU Guidelines on Prostate Cancer - Uroweb [Internet]. 2026 [cited 2026 Mar 23]. Available from: https://uroweb.org/guidelines/prostate-cancer
Cornu JN, Gacci M, Hashim H, Herrmann TRW, Malde S, Netsch C, et al. EAU Guidelines on Non Neurogenic Male LUTS [Internet]. European Association of Urology; 2025 [cited 2025 Jul 8]. Available from: https://d56bochluxqnz.cloudfront.net/documents/full-guideline/EAU-Guidelines-on-Non-Neurogenic-Male-LUTS-2025.pdf
Dovey Z, Horowitz A, Waingankar N. The influence of lifestyle changes (diet, exercise and stress reduction) on prostate cancer tumour biology and patient outcomes: A systematic review. BJUI Compass. 2023;4(4):385–416. doi:10.1002/bco2.237
Foerster B, Pozo C, Abufaraj M, Mari A, Kimura S, D’Andrea D, et al. Association of Smoking Status With Recurrence, Metastasis, and Mortality Among Patients With Localized Prostate Cancer Undergoing Prostatectomy or Radiotherapy: A Systematic Review and Meta-analysis. JAMA Oncol. 2018 Jul 1;4(7):953–61. doi:10.1001/jamaoncol.2018.1071
Frazzoni L, La Marca M, Guido A, Morganti AG, Bazzoli F, Fuccio L. Pelvic radiation disease: Updates on treatment options. World J Clin Oncol. 2015 Dec 10;6(6):272–80. doi:10.5306/wjco.v6.i6.272 PubMed PMID: 26677440; PubMed Central PMCID: PMC4675912.
Ghaffar U, Abbasi B, Li KD, Venishetty N, Hakam N, Fernandez A, et al. Ejaculatory function after radiotherapy for prostate cancer: a systematic review and meta-analysis. Prostate Cancer Prostatic Dis. 2025 Sep;28(3):572–7. doi:10.1038/s41391-024-00882-4
Gianotten WL. Sexual aspects of shared decision making and prehabilitation in men diagnosed with prostate cancer. Int J Impot Res. 2021 May;33(4):397–400. doi:10.1038/s41443-020-00404-5
Guy’s and St Thomas’ NHS Foundation Trust [Internet]. [cited 2026 Jul 13]. How drinks affect your bladder and bowel - Overview. Available from: https://www.guysandstthomas.nhs.uk/health-information/how-drinks-affect-your-bladder-and-bowel
Hamblen AJ, Bray JW, Hingorani M, Saxton JM. Physical activity and dietary considerations for prostate cancer patients: future research directions. Proc Nutr Soc. 2023 Sep;82(3):298–304. doi:10.1017/S0029665123000046
Henry A, Pieters BR, Siebert FA, Hoskin P. GEC-ESTRO ACROP prostate brachytherapy guidelines. Radiother Oncol. 2022 Feb 1;167:244–51. doi:10.1016/j.radonc.2021.12.047 PubMed PMID: 34999134.
Human Fertilisation & Embryology Authority (HFEA). Human Fertilisation & Embryology Authority (HFEA) [Internet]. [cited 2025 Aug 6]. Sperm freezing. Available from: https://www.hfea.gov.uk/treatments/fertility-preservation/sperm-freezing/
Hunt AA, Choudhury KR, Nukala V, Nolan MW, Ahmad A, Ashcraft KA, et al. Risk of erectile dysfunction after modern radiotherapy for intact prostate cancer. Prostate Cancer Prostatic Dis. 2021 Mar;24(1):128–34. doi:10.1038/s41391-020-0247-x
Huyghe E, Delannes M, Wagner F, Delaunay B, Nohra J, Thoulouzan M, et al. Ejaculatory Function After Permanent 125I Prostate Brachytherapy for Localized Prostate Cancer. Int J Radiat Oncol. 2009 May;74(1):126–32. doi:10.1016/j.ijrobp.2008.07.064
Ishiyama H, Hirayama T, Jhaveri P, Satoh T, Paulino AC, Xu B, et al. Is There an Increase in Genitourinary Toxicity in Patients Treated With Transurethral Resection of the Prostate and Radiotherapy?: A Systematic Review. Am J Clin Oncol. 2014 Jun;37(3):297–304. doi:10.1097/COC.0b013e3182546821
Jassem J. Tobacco smoking after diagnosis of cancer: clinical aspects. Transl Lung Cancer Res. 2019 May;8(S1):S50–8. doi:10.21037/tlcr.2019.04.01
Johnson EE, Mamoulakis C, Stoniute A, Omar MI, Sinha S. Conservative interventions for managing urinary incontinence after prostate surgery. Cochrane Database Syst Rev. 2023;2023(4). doi:10.1002/14651858.cd014799.pub2
King MT, Keyes M, Frank SJ, Crook JM, Butler WM, Rossi PJ, et al. Low dose rate brachytherapy for primary treatment of localized prostate cancer: A systemic review and executive summary of an evidence-based consensus statement. Brachytherapy. 2021 Nov;20(6):1114–29. doi:10.1016/j.brachy.2021.07.006
Kishan A, Kupelian P. Late rectal toxicity after low-dose-rate brachytherapy: incidence, predictors, and management of side effects. Brachytherapy. 2014;14(2):148–59.
Kubo K, Wadasaki K, Kimura T, Murakami Y, Kajiwara M, Teishima J, et al. Clinical features of prostate-specific antigen bounce after 125I brachytherapy for prostate cancer. J Radiat Res (Tokyo). 2018 Sep 1;59(5):649–55. doi:10.1093/jrr/rry059
Kwon WA, Lee SY, Jeong TY, Moon HS. Lower Urinary Tract Symptoms in Prostate Cancer Patients Treated With Radiation Therapy: Past and Present. Int Neurourol J. 2021 Jun 30;25(2):119–27. doi:10.5213/inj.2040202.101
Langley SEM, Laing RW. 4D Brachytherapy, a novel real-time prostate brachytherapy technique using stranded and loose seeds. BJU Int. 2012;109(s1):1–6. doi:10.1111/j.1464-410X.2011.10824.x
Langley SEM, Soares R, Uribe J, Uribe-Lewis S, Money-Kyrle J, Perna C, et al. Long-term oncological outcomes and toxicity in 597 men aged ≤60 years at time of low-dose-rate brachytherapy for localised prostate cancer. BJU Int. 2018;121(1):38–45. doi:10.1111/bju.13946
Lardas M, Liew M, van den Bergh RC, De Santis M, Bellmunt J, Van den Broeck T, et al. Quality of Life Outcomes after Primary Treatment for Clinically Localised Prostate Cancer: A Systematic Review. Eur Urol. 2017 Dec;72(6):869–85. doi:10.1016/j.eururo.2017.06.035
Lehto US, Tenhola H, Taari K, Aromaa A. Patients’ perceptions of the negative effects following different prostate cancer treatments and the impact on psychological well-being: a nationwide survey. Br J Cancer. 2017 Mar 28;116(7):864–73. doi:10.1038/bjc.2017.30
Lippens J, Willems L, Boychak O, Pinkawa M, Orio PF, Chao MWT, et al. Implantable Rectal Spacers in Prostate Cancer Radiation Therapy: A Systematic Review. Pract Radiat Oncol. 2025 Sep 1;15(5):e460–83. doi:10.1016/j.prro.2025.03.009 PubMed PMID: 40246071.
Lischalk JW, Blacksburg S, Mendez C, Repka M, Sanchez A, Carpenter T, et al. Stereotactic body radiation therapy for the treatment of localized prostate cancer in men with underlying inflammatory bowel disease. Radiat Oncol. 2021 Dec;16(1):126. doi:10.1186/s13014-021-01850-1
Luo YH, Yang YW, Wu CF, Wang C, Li WJ, Zhang HC. Fatigue prevalence in men treated for prostate cancer: A systematic review and meta-analysis. World J Clin Cases. 2021 Jul 26;9(21):5932–42. doi:10.12998/wjcc.v9.i21.5932
Maletzki P, Schwab C, Markart P, Engeler D, Schiefer J, Plasswilm L, et al. Late seed migration after prostate brachytherapy with Iod-125 permanent implants. Prostate Int. 2018 Jun;6(2):66–70. doi:10.1016/j.prnil.2017.09.003
Mazzone E, Mistretta FA, Knipper S, Palumbo C, Tian Z, Pecoraro A, et al. Long-Term Incidence of Secondary Bladder and Rectal Cancer in Patients Treated with Brachytherapy for Localized Prostate Cancer: A Large-Scale Population-Based Analysis. BJU Int. 2019 May 30. doi:10.1111/bju.14841
McInnis MK, Pukall CF. Sex After Prostate Cancer in Gay and Bisexual Men: A Review of the Literature. Sex Med Rev. 2020 Jul;8(3):466–72. doi:10.1016/j.sxmr.2020.01.004
Michalski J, Mutic S, Eichling J, Ahmed SN. Radiation exposure to family and household members after prostate brachytherapy. Int J Radiat Oncol. 2003 Jul;56(3):764–8. doi:10.1016/S0360-3016(03)00002-6
Morris KA, Haboubi NY. Pelvic radiation therapy: Between delight and disaster. World J Gastrointest Surg. 2015 Nov 27;7(11):279–88. doi:10.4240/wjgs.v7.i11.279 PubMed PMID: 26649150; PubMed Central PMCID: PMC4663381.
Morris WJ, Tyldesley S, Rodda S, Halperin R, Pai H, McKenzie M, et al. Androgen Suppression Combined with Elective Nodal and Dose Escalated Radiation Therapy (the ASCENDE-RT Trial): An Analysis of Survival Endpoints for a Randomized Trial Comparing a Low-Dose-Rate Brachytherapy Boost to a Dose-Escalated External Beam Boost for High- and Intermediate-risk Prostate Cancer. Int J Radiat Oncol Biol Phys. 2017 Jun 1;98(2):275–85. doi:10.1016/j.ijrobp.2016.11.026 PubMed PMID: 28262473.
Muraki K, Nakiri M, Purysko AS, Hattori C, Suefuji H, Suekane H, et al. Permanent Prostate Brachytherapy Placement: Imaging Assessment of Seed Positioning, Spacer Use, and Complications. RadioGraphics. 2025 Dec 1;45(12):e250051. doi:10.1148/rg.250051
National Institute for Health and Care Excellence. Prostate cancer: diagnosis and management. NICE Guideline 131 [Internet]. 2021. Available from: https://www.nice.org.uk/guidance/ng131/resources/prostate-cancer-diagnosis-and-management-pdf-66141714312133
National Institute for Health and Clinical Excellence. Biodegradable spacer insertion to reduce rectal toxicity during radiotherapy for prostate cancer [Internet]. 2023. Available from: https://www.nice.org.uk/guidance/ipg752
Nguyen DD, Berlin A, Matthew AG, Perlis N, Elterman DS. Sexual function and rehabilitation after radiation therapy for prostate cancer: a review. Int J Impot Res. 2021 May;33(4):410–7. doi:10.1038/s41443-020-00389-1
Niwa K, Iinuma K, Nakano M, Tomioka M, Ito M, Mori T, et al. Secondary primary tumors following iodine-125 low-dose-rate brachytherapy for localized prostate cancer. Int J Clin Oncol. 2026 Mar 29. doi:10.1007/s10147-026-03020-3
Nolsøe AB, Jensen CFS, Østergren PB, Fode M. Neglected side effects to curative prostate cancer treatments. Int J Impot Res. 2021 May;33(4):428–38. doi:10.1038/s41443-020-00386-4
Nugent TS, Low EZ, Fahy MR, Donlon NE, McCormick PH, Mehigan BJ, et al. Prostate radiotherapy and the risk of secondary rectal cancer—a meta-analysis. Int J Colorectal Dis. 2022 Feb;37(2):437–47. doi:10.1007/s00384-021-04075-6
Numakura K, Kobayashi M, Muto Y, Sato H, Sekine Y, Sobu R, et al. The Current Trend of Radiation Therapy for Patients with Localized Prostate Cancer. Curr Oncol. 2023 Aug 31;30(9):8092–110. doi:10.3390/curroncol30090587
Peinemann F, Grouven U, Bartel C, Sauerland S, Borchers H, Pinkawa M, et al. Permanent Interstitial Low-Dose-Rate Brachytherapy for Patients with Localised Prostate Cancer: A Systematic Review of Randomised and Nonrandomised Controlled Clinical Trials. Eur Urol. 2011 Nov;60(5):881–93. doi:10.1016/j.eururo.2011.06.044
Ralph S. Developing UK Guidance on How Long Men Should Abstain from Receiving Anal Sex before, During and after Interventions for Prostate Cancer. Clin Oncol. 2021 Dec;33(12):807–10. doi:10.1016/j.clon.2021.07.010
Razdan S, Pandav K, Altschuler J, Moody K, Martin L, Patel HD, et al. Impact of exercise on continence in prostate cancer patients post robotic assisted radical prostatectomy: a systematic review. Am J Clin Exp Urol. 2023 Aug 15;11(4):320–7. PubMed PMID: 37645610; PubMed Central PMCID: PMC10461030.
Royal College of Radiologists. Quality assurance practice guidelines for transperineal LDR permanent seed brachytherapy of prostate cancer. 2012.
Solanki AA, Liauw SL. Tobacco use and external beam radiation therapy for prostate cancer: Influence on biochemical control and late toxicity: Prostate Radiation Toxicity in Smokers. Cancer. 2013 Aug 1;119(15):2807–14. doi:10.1002/cncr.28128
Sterling J, Rahman SN, Varghese A, Angulo JC, Nikolavsky D. Complications after Prostate Cancer Treatment: Pathophysiology and Repair of Post-Radiation Urethral Stricture Disease. J Clin Med. 2023 Jun 9;12(12):3950. doi:10.3390/jcm12123950
Stish BJ, Davis BJ, Mynderse LA, McLaren RH, Deufel CL, Choo R. Low dose rate prostate brachytherapy. Transl Androl Urol. 2018 Jun;7(3):341–56. doi:10.21037/tau.2017.12.15 PubMed PMID: 30050795; PubMed Central PMCID: PMC6043740.
St-Laurent, MP, et al. Long-Term Second Malignancies in Prostate Cancer Patients Treated With Low-Dose-Rate Brachytherapy and Radical Prostatectomy | Journal of Urology. J Urol [Internet]. 2024 Apr 29 [cited 2026 May 18]. Available from: https://www.auajournals.org/doi/10.1097/JU.0000000000003965
Tran S, Boissier R, Perrin J, Karsenty G, Lechevallier E. Review of the Different Treatments and Management for Prostate Cancer and Fertility. Urology. 2015 Nov;86(5):936–41. doi:10.1016/j.urology.2015.07.010
Trotta M, Patel KR, Singh S, Verma V, Ryckman J. Safety of Radiation Therapy in Patients With Prostate Cancer and Inflammatory Bowel Disease: A Systematic Review. Pract Radiat Oncol. 2023 Sep;13(5):454–65. doi:10.1016/j.prro.2023.04.006
Uribe-Lewis S, Uribe J, Bourke V, Deering C, Higgins D, Mehta S, et al. Long-term survival after low-dose-rate brachytherapy for prostate cancer: the Royal Surrey experience. BJU Int. 2022;129(6):723–30. doi:10.1111/bju.15585
Uribe-Lewis S, Uribe J, Deering C, Langley S, Higgins D, Whiting D, et al. Net survival of men with localized prostate cancer after LDR brachytherapy. Brachytherapy. 2024 May;23(3):329–34. doi:10.1016/j.brachy.2024.02.006
Wang L, Wu L, Qian C, Ju Y, Liu T, Chen Y, et al. The Beneficial Effect of a Healthy Dietary Pattern on Androgen Deprivation Therapy-Related Metabolic Abnormalities in Patients with Prostate Cancer: A Meta-Analysis Based on Randomized Controlled Trials and Systematic Review. Metabolites. 2022 Oct 13;12(10):969. doi:10.3390/metabo12100969
Warli S, Ikram MF, Kadar D, Siregar G, Prapiska F, Laksmi LI, et al. The Radical Prostatectomy Versus Brachytherapy for the Management of Low- and Intermediate-Risk Prostate Cancer: A Meta-Analysis of Observational Studies Focusing on Oncological Outcomes. Asian Pac J Cancer Prev. 2026 Jan 1;27(1):233–48. doi:10.31557/APJCP.2026.27.1.233
Wedlake LJ. Nutritional strategies to prevent gastrointestinal toxicity during pelvic radiotherapy. Proc Nutr Soc. 2018 Nov;77(4):357–68. doi:10.1017/s0029665118000101
White ID. Sexual Difficulties after Pelvic Radiotherapy: Improving Clinical Management. Clin Oncol. 2015 Nov;27(11):647–55. doi:10.1016/j.clon.2015.06.018
Wolff RF, Ryder S, Bossi A, Briganti A, Crook J, Henry A, et al. A systematic review of randomised controlled trials of radiotherapy for localised prostate cancer. Eur J Cancer. 2015 Nov;51(16):2345–67. doi:10.1016/j.ejca.2015.07.019
Yuan F, Wang Y, Xiao X, Zhang X, Jing M, Kamecki H, et al. A systematic review evaluating the effectiveness of exercise training on physical condition in prostate cancer patients undergoing androgen deprivation therapy. Transl Androl Urol. 2023 Aug 31;12(8):8. doi:10.21037/tau-23-272
Zaorsky NG, Shaikh T, Murphy CT, Hallman MA, Hayes SB, Sobczak ML, et al. Comparison of outcomes and toxicities among radiation therapy treatment options for prostate cancer. Cancer Treat Rev. 2016 Jul;48:50–60. doi:10.1016/j.ctrv.2016.06.006
This publication was written and edited by our Health Information team.
It was reviewed by:
Peter Bownes, Consultant Clinical Scientist, Leeds Teaching Hospitals NHS Trust
Richard Gledhill, Prostate Cancer Nurse Specialist, University Hospitals Birmingham
Ann Henry, Clinical Oncologist, Leeds Teaching Hospitals NHS Trust
Stephen Langley, Clinical Urologist, Royal Surrey Cancer Centre & NHS Hospital
Our Specialist Nurses
Our volunteers.
